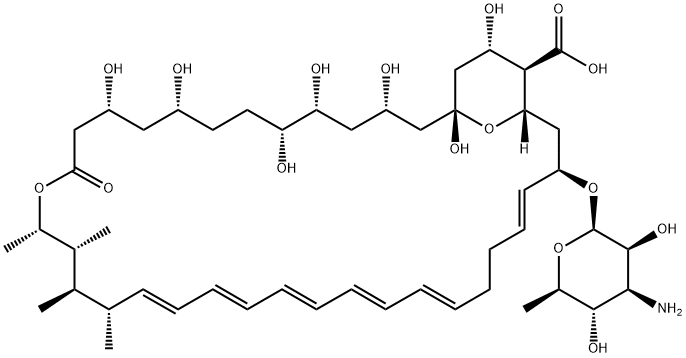
Description
Amphotericin B (1397-89-3) is a powerful antimycotic, effective against a wide variety of fungi, including yeast, via two mechanisms: forming pores in the plasma membrane, leading to leakage and death1, and causing oxidative stress2. Other mechanisms have more recently been proposed, including formation of intracellular amphotericin B-containing vesicular bodies that target vacuoles.3 Amphotericin B is also effective against some parasites, such as Leishmania spp.4 Because of its potency and broad-spectrum activity, it is a common additive used to maintain sterility in cell culture and viral transport media.
Originator
Fungizone,Squibb,US,1958
Definition
ChEBI: A macrolide antibiotic used to treat potentially life-threatening fungal infections.
Manufacturing Process
The process for producing amphotericin comprises cultivating a strain of
Streptomyces nodosus in an aqueous nutrient medium comprising an
assimilable, fermentable carbohydrate and an assimilable organic nitrogen
source, under submerged aerobic conditions, until substantial antifungal
activity is imparted to the medium and recovering amphotericin from the
medium.
Brand name
Amphotec (Three Rivers); Fungizone (BristolMyers
Squibb).
Therapeutic Function
Antifungal
Antimicrobial activity
The spectrum includes most fungi that cause human disease:
A. fumigatus, Blast. dermatitidis, Candida spp., Coccidioides spp.,
Cryptococcus spp., Hist. capsulatum, Paracocc. brasiliensis and Spor.
schenckii. Dermatophytes, Fusarium spp. and some other Aspergillus
spp., including A. terreus and A. flavus, may be less susceptible,
while Scedosporium spp., Trichosporon asahii (formerly T. beigelii)
and some fungi that cause mucormycosis are resistant.
Acquired resistance
Resistant strains of C. tropicalis, C. lusitaniae, C. krusei and C.
guilliermondii, with alterations in the cell membrane, including
reduced amounts of ergosterol, have occasionally been isolated
after prolonged treatment, particularly of infections in
partially protected sites, such as the vegetations of endocarditis.
Significant resistance in yeasts, including C. albicans and
C. glabrata, has been reported in isolates from cancer patients
with prolonged neutropenia. In some cases resistant strains
have caused disseminated infection. There are a few reports of
amphotericin-resistant strains of Cryp. neoformans recovered
from AIDS patients with relapsed meningitis.
Hazard
May have undesirable side effects.
Pharmaceutical Applications
A fermentation product of Streptomyces nodosus available for
intravenous infusion or oral administration. The traditional
micellar suspension formulation is often associated with serious
toxic effects, in particular renal damage, and this has
stimulated efforts to develop chemical modifications and new
formulations.
Biochem/physiol Actions
Amphotericin B is used for primary treatment of acute invasive fungal infections, such as aspergillosis.
Pharmacokinetics
Less than 10% of a parenteral dose of the conventional micellar
suspension of amphotericin B remains in the blood 12 h
after administration. The remainder is thought to bind to tissue
cell membranes, the highest concentrations being found
in the liver (up to 40% of the dose). Levels in the CSF are
less than 5% of the simultaneous blood concentration. The
conventional formulation has a terminal half-life of about 2
weeks. About 75% of a given dose is excreted unchanged in
the urine and feces. No metabolites have been identified.
The pharmacokinetics of lipid-based formulations are
quite diverse. Maximal serum concentrations of
the liposomal formulation are much higher than those of the
conventional micellar formulation, while levels of colloidal
dispersion and lipid complex formulations are lower due to
more rapid distribution of the drug to tissue. Administration
of lipid-associated formulations of amphotericin B results in
much higher drug concentrations in the liver and spleen than
are achieved with the conventional formulation. Renal concentrations
of the drug are much lower and its nephrotoxic
side effects are greatly reduced.
Blood concentrations are unchanged in hepatic or renal
failure. Hemodialysis does not influence serum concentrations
unless the patient is hyperlipidemic, in which case
there is some drug loss due to adherence to the dialysis
membrane.
Pharmacology
This compound has a broad spectrum of antifungal activity, including Candida albicans,
Leishmania brasiliensis, Mycobacterium leprae, Histoplasma capsulatum, Blastomyces
dermatitidus, and Coccidioides immitis. It possesses fungistatic and fungicidal activity
depending on the dose used. The antifungal activity of amphotericin B is exhibited
because it binds with sterols, in particular with ergosterol in the cellular membrane of
sensitive fungi. This reaction makes pores in the membrane and increases the perme�ability of the membrane to small molecules, thus reducing the function of the membrane
as an osmotic barrier and making the cells more sensitive to being destroyed.
Amphotericin B is active against growing cells and cells that are dormant. However, this
compound is not highly selective and reacts with host mammalian cells. Despite the
many side effects, amphotericin B remains the primary drug for treating severe, acute
systemic fungal infections. It is used for generalized fungal infections, such as can�didomycosis, aspergillosis, histoplasmosis, cryptococcosis, coccidioidomycosis, blasto�mycosis, and pulmonary mycoses. Synonyms of this drug are amphocyclin, fungisone,
fungilin, and others.
Clinical Use
Amphotericin B(1397-89-3) is most commonly used to treat serious
disseminated yeast and dimorphic fungal infections in
immunocompromised hospitalized patients. As additional
experience has been gained in the treatment of
fungal infections with the newer azoles, the use of amphotericin
B has diminished; if azole drugs have equivalent
efficacy, they are preferred to amphotericin B because
of their reduced toxicity profile and ease of
administration. For the unstable neutropenic patient
with Candida albicans fungemia, amphotericin B is the
drug of choice.
Amphotericin B remains the drug of choice in the
treatment of invasive aspergillosis, locally invasive mucormycosis,
and many disseminated fungal infections
occurring in immunocompromised hosts (the patient
population most at risk for serious fungal infections).
For example, the febrile neutropenic oncology patient
with persistent fever despite empirical antibacterial
therapy is best treated with amphotericin B for possible
Candida spp. sepsis.
Clinical Use
Aspergillosis
Systemic mycoses with dimorphic fungi (blastomycosis,
coccidioidomycosis, histoplasmosis, paracoccidioidomycosis, penicilliosis)
Candidosis
Cryptococcosis
Hyalohyphomycosis, mucormycosis, phaeohyphomycosis
Visceral leishmaniasis
Synthesis
Amphotericin B, is a large polyene antibiotic made from the cultural fluid of the actino�mycete Streptomyces nodosus.
Veterinary Drugs and Treatments
Amphotericin B has been used topically and subconjunctivally to
treat cases of equine fungal keratitis. Amphotericin B is fungistatic
or fungicidal depending on the concentration obtained in body fluids
and the susceptibility of the fungus. The drug acts by binding
to sterols in the cell membrane of susceptible fungi with a resultant
change in membrane permeability allowing leakage of intracellular
components. Mammalian cell membranes also contain sterols and
it has been suggested that the damage to human cells and fungal
cells may share common mechanisms. Amphotericin B has been
shown to be effective against the following fungi: Histoplasma capsulatum,
Coccidioides immitis, Candida species, Blastomyces dermatitidis,
Rhodotorula, Cryptococcus neoformans, Sporothrix schenckii,
Mucor mucedo, and Aspergillus fumigatus. While Candida albicans is
generally quite susceptible to amphotericin B, non-albicans species
may be less susceptible. Pseudallescheria boydii and Fusarium spp.
are often resistant to amphotericin B. The major action of amphotericin
B is to bind ergosterol in the fungal plasma cell membrane,
making the membrane more permeable and resulting in leakage of
cell electrolytes and cell death. At high concentrations, amphotericin
B is thought to cause oxidative damage to the fungal cell or disruption
of fungal cell enzymes.
in vitro
amphotericin b was the most effective drug for treating many life-threatening fungal infections. in cells expressing tlr2 and cd14, amphotericin b induced signal transduction and inflammatory cytokine release. in primary murine macrophages and human cell lines expressing tlr2, cd14, and the adapter protein myd88, amphotericin induced nf-κb-dependent reporter activity and cytokine release, whereas cells deficient in any of these failed to respond. cells with tlr4 mutation were less responsive to amphotericin b stimulation than cells expressing normal tlr4 [1]. amphotericin b could interact with cholesterol, the major sterol of mammal membranes, thus limiting the usefulness of amphotericin b due to its relatively high toxicity [2]. low amb concentrations (≤ 0.1 μm) induced a polarization potential in kcl-loaded liposomes suspended in an iso-osmotic sucrose solution, indicating k+ leakage. amb (> 0.1 μm) allowed cations and anions movements. lps suspended in an iso-osmotic nacl solution and exposed to amb (0.05 μm) exhibited a nearly total collapse of the negative membrane potential, indicated that na+ entered into the cells [3].
in vivo
amphotericin b prolonged the incubation time and decreased prpsc accumulation in the hamster scrapie model. amphotericin b markedly resulted in reduction of prpsc levels in mice with transmissible subacute spongiform encephalopathies (tsse) [4].
target
NO | PKA | IL Receptor | TNF-α | p38MAPK | ERK | PGE
storage
4°C, protect from light