
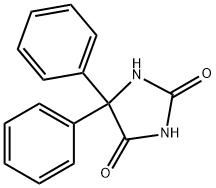
General Description
Fine white or almost white crystalline powder. Odorless or almost odorless. Tasteless.
Reactivity Profile
PHENYTOIN(57-41-0) is an amide. Amides/imides react with azo and diazo compounds to generate toxic gases. Flammable gases are formed by the reaction of organic amides/imides with strong reducing agents. Amides are very weak bases (weaker than water). Imides are less basic yet and in fact react with strong bases to form salts. That is, they can react as acids. Mixing amides with dehydrating agents such as P2O5 or SOCl2 generates the corresponding nitrile. The combustion of these compounds generates mixed oxides of nitrogen (NOx). This chemical is incompatible with strong oxidizers and strong bases.
Air & Water Reactions
Insoluble in water.
Potential Exposure
Phenytoin is an amide pharmaceutical used in the treatment of grand mal epilepsy, Parkinson’s syndrome; and in veterinary medicine. Human exposure to phenytoin occurs principally during its use as a drug. Figures on the number of patients using phenytoin are not available, but phenytoin is given to a major segment of those individuals with epilepsy. The oral dose rate is initially 100 mg given 3 times per day and can gradually increase by 100 mg every 24 weeks until the desired therapeutic response is obtained. The intravenous dose is 200350 mg/day.
Fire Hazard
Flash point data for this chemical are not available; however, PHENYTOIN is probably combustible.
First aid
Skin Contact: Flood all areas of body that have contacted the substance with water. Don’t wait to remove contaminated clothing; do it under the water stream. Use soap to help assure removal. Isolate contaminated clothing when removed to prevent contact by others. Eye Contact: Remove any contact lenses at once. Flush eyes well with copious quantities of water or normal saline for at least 2030 minutes. Seek medical attention. Inhalation: Leave contaminated area immediately; breathe fresh air. Proper respiratory protection must be supplied to any rescuers. If coughing, difficult breathing or any other symptoms develop, seek medical attention at once, even if symptoms develop many hours after exposure. Ingestion: If convulsions are not present, give a glass or two of water or milk to dilute the substance. Assure that the person’s airway is unobstructed and contact a hospital or poison center immediately for advice on whether or not to induce vomiting.
Shipping
UN2811 Toxic solids, organic, n.o.s., Hazard Class: 6.1; Labels: 6.1-Poisonous materials, Technical Name Required. UN3249 Medicine, solid, toxic, n.o.s., Hazard Class: 6.1; Labels: 6.1-Poisonous materials.
Incompatibilities
Incompatible with oxidizers (chlorates, nitrates, peroxides, permanganates, perchlorates, chlorine, bromine, fluorine, etc.); contact may cause fires or explosions. Keep away from alkaline materials, strong bases, strong acids, oxoacids, epoxides. Similar organic amides react with azo and diazo compounds, releasing toxic gases. Contact with reducing agents can release flammable gases. Amides are very weak bases but they can react as acids, forming salts. Mixing amides with dehydrating agents such as phosphorus pentoxide or thionyl chloride generates the corresponding nitrile.
Chemical Properties
Phenytoin is a crystalline compound
Chemical Properties
white crystals or powder
Originator
Dilantin ,Parke Davis ,US ,1938
Uses
5,5-Diphenylhydantoin has been used for phenytoin treatment. It has also been used to slow down or prevent mesoendoderm cell migration.
Uses
A sodium channel protein inhibitor
Uses
Phenytoin has the same main effects on the heart as lidocaine. Its use is essentially limited,
and it is primarily used only as an oral replacement of lidocaine for paroxysmal tachycardia
that is caused particularly by intoxication of digitalis drugs.
Uses
Reduces incidence of grand mal seizures; appears to stabilize excitable membranes perhaps through effects on Na+, K+, and Ca2+ channels.
Definition
ChEBI: A imidazolidine-2,4-dione that consists of hydantoin bearing two phenyl substituents at position 5.
Manufacturing Process
10 g of benzophenone (1 mol), 4 g of potassium cyanide (1.22 mols) and 16 g of ammonium carbonate (3.3 mols) are dissolved in 100 cc of 60% (by volume) ethyl alcohol and the mixture warmed under a reflux condenser without stirring at 58° to 62°C. After warming the mixture for 10 hours apartial vacuum is applied and the temperature is raised enough to permit concentration of the reaction mixture to two-thirds of its initial volume.
A slight excess of mineral acid, such as sulfuric or hydrochloric acid is added to acidify the mixture which is then chilled and the solid which separates is filtered off. It is then treated with an aqueous solution of dilute sodium hydroxide to dissolve the hydantoin from the solid unreacted benzophenone. After filtration, the alkaline extract is then acidified to cause the separation of solid pure diphenylhydantoin which is filtered off and dried. It melts at 293° to 296°C.
A net yield of about 95% is obtained by the procedure described above. If the time of warming the reaction mixture is increased three-or four-fold, practically 100% net yields are obtained. The same high net yields are also obtained by heating for even longer periods of time. For example, by heating for 90 hours, a 100% net yield, or 67% gross yield, is obtained.
Brand name
Anticonvulsant.
Dilantin (Pfizer) [Name previously used:
Diphenylhydantoin.].
Therapeutic Function
Antiepileptic
Biological Functions
Phenytoin is a valuable agent for the treatment of generalized
tonic–clonic seizures and for the treatment of
partial seizures with complex symptoms. The establishment
of phenytoin (at that time known as diphenylhydantoin)
in 1938 as an effective treatment for epilepsy
was more than simply the introduction of another drug
for treatment of seizure disorders. Until that time the
only drugs that had any beneficial effects in epilepsy
were the bromides and barbiturates, both classes of
compounds having marked CNS depressant properties.
The prevailing view among neurologists of that era was
that epilepsy was the result of excessive electrical activity in the brain and it therefore seemed perfectly reasonable
that CNS depressants would be effective in antagonizing
the seizures. Consequently,many patients received
high doses of barbiturates and spent much of
their time sedated. Also, since CNS depression was considered
to be the mechanism of action of AEDs, the
pharmaceutical firms were evaluating only compounds
with profound CNS depressant properties as potential antiepileptic agents. It was, therefore, revolutionary
when phenytoin was shown to be as effective as phenobarbital
in the treatment of epilepsy without any significant
CNS depressant activity. This revolutionized the
search for new anticonvulsant drugs as well as immediately
improving the day-to-day functioning of epileptic
patients.
An understanding of absorption, binding, metabolism,
and excretion is more important for phenytoin
than it is for most drugs. Following oral administration,
phenytoin absorption is slow but usually complete, and
it occurs primarily in the duodenum. Phenytoin is highly
bound (about 90%) to plasma proteins, primarily
plasma albumin. Since several other substances can also
bind to albumin, phenytoin administration can displace
(and be displaced by) such agents as thyroxine, triiodothyronine,
valproic acid, sulfafurazole, and salicylic
acid.
Mechanism of action
Phenytoin is indicated for initial monotherapy or adjunct treatment of complex partial or tonic-clonic seizures, convulsive status
epilepticus, and prophylaxis. It often is selected for initial monotherapy because of its high efficacy and relatively low incidence
of side effects. Phenytoin is not used in the treatment of absence seizures, because it may increase their frequency of
occurrence. Phenytoin binds to and stabilizes the inactivated state of sodium channels, thus producing a
use-dependent blockade of repetitive firing and inhibition of the spread of seizure activity to adjacent cortical areas.
Pharmacokinetics
Phenytoin may be administered either orally or intravenously and is absorbed slowly after oral
administration, with peak plasma levels achieved after 3 to 12 hours. It is extensively plasma protein
bound (~90%), and the elimination half-life is between 15 and 30 hours. These large ranges reflect
the considerable variability observed from patient to patient. Parenteral administration of phenytoin
is usually limited to the intravenous route. Phenytoin for injection is dissolved in a highly alkaline
vehicle (pH 12). This alkaline vehicle is required because phenytoin is weakly acidic and has very
poor solubility in its un-ionized form. Reportedly, however, its phosphate ester fosphenytoin has
water solubility advantages over phenytoin for injection. Intramuscular phenytoin generally is
avoided, because it results in tissue necrosis at the site of injection and erratic absorption because
of high alkalinity. In addition, intermittent intravenous infusion is required to reduce the incidence of
severe phlebitis.
Phenytoin metabolism is relatively slow and predominantly involves aromatic hydroxylation to
p-hydroxylated inactive metabolites. Phenytoin also induces its own metabolism
and is subject to large interindividual variability. The major metabolite, 5-p-hydroxyphenyl-
5-phenylhydantoin, accounts for approximately 75% of a dose. This metabolite is excreted through
the kidney as the β-glucuronide conjugate. Phenytoin clearance is strongly influenced by its
metabolism; therefore, agents that affect phenytoin metabolism may cause intoxication. In addition,
because phenytoin is highly plasma protein bound, agents that displace phenytoin also may cause
toxicity.
Pharmacology
In terms of its effect on the CNS, phenytoin is considered an excellent antiepileptic drug
with insignificant sedative effects. Even in large doses it does not cause hypnosis. It is presumed that phenytoin facilitates secretion of sodium ions from nerve cells, which reduces
the stimulation of neurons. This in turn prevents the activation of neurons upon receiving
impulses from the epileptogenic center. In addition, phenytoin reduces the incoming flow
of potassium ions during repolarization. It is possible that phenytoin significantly slows the
distribution of excitation in the brain as a direct result of the redistribution of the ion flow.
Clinical Use
Phenytoin (Dilantin) was originally introduced for the
control of convulsive disorders but has
now also been shown to be effective in the treatment of
cardiac arrhythmias. Phenytoin appears to be particularly
effective in treating ventricular arrhythmias in children.
Phenytoin, like lidocaine, is more effective in the treatment
of ventricular than supraventricular arrhythmias.
It is particularly effective in treating ventricular arrhythmias
associated with digitalis toxicity, acute myocardial
infarction, open-heart surgery, anesthesia, cardiac
catheterization, cardioversion, and angiographic
studies.
Phenytoin finds its most effective use in the treatment
of supraventricular and ventricular arrhythmias
associated with digitalis intoxication. The ability of
phenytoin to improve digitalis-induced depression of
A-V conduction is a special feature that contrasts with
the actions of other antiarrhythmic agents.
Clinical Use
Phenytoin is one of very few drugs that displays
zero-order (or saturation) kinetics in its metabolism.At
low blood levels the rate of phenytoin metabolism is
proportional to the drug’s blood 1evels (i.e., first-order
kinetics). However, at the higher blood levels usually
required to control seizures, the maximum capacity of
drug-metabolizing enzymes is often exceeded (i.e., the
enzyme is saturated), and further increases in the dose
of phenytoin may lead to a disproportionate increase in
the drug’s blood concentration. Since the plasma levels
continue to increase in such a situation, steady-state levels
are not attained, and toxicity may ensue. Calculation
of half-life (t1/2) values for phenytoin often is meaningless,
since the apparent half-life varies with the drug
blood level.
Acute adverse effects seen after phenytoin administration
usually result from overdosage. They are generally
characterized by nystagmus, ataxia, vertigo, and
diplopia (cerebellovestibular dysfunction). Higher
doses lead to altered levels of consciousness and cognitive
changes.
A variety of idiosyncratic reactions may be seen
shortly after therapy has begun. Skin rashes, usually
morbilliform in character, are most common.
Exfoliative dermatitis or toxic epidermal necrolysis
(Lyellís syndrome) has been observed but is infrequent.
Other rashes occasionally have been reported, as have a
variety of blood dyscrasias and hepatic necrosis.
Side effects
The most common side effect in children receiving
long-term therapy is gingival hyperplasia, or overgrowth
of the gums (occurs in up to 50% of patients).
Although the condition is not serious, it is a cosmetic
problem and can be very embarrassing to the patient.
Hirsutism also is an annoying side effect of phenytoin,
particularly in young females. Thickening of subcutaneous
tissue, coarsening of facial features, and enlargement
of lips and nose (hydantoin facies) are often seen
in patients receiving long-term phenytoin therapy.
Peripheral neuropathy and chronic cerebellar degeneration
have been reported, but they are rare.
There is evidence that phenytoin is teratogenic in
humans, but the mechanism is not clear. However, it is
known that phenytoin can produce a folate deficiency,
and folate deficiency is associated with teratogenesis.
Only a few well-documented drug combinations
with phenytoin may necessitate dosage adjustment.
Coadministration of the following drugs can result in
elevations of plasma phenytoin levels in most patients:
cimetidine, chloramphenicol, disulfiram, sulthiame, and
isoniazid (in slow acetylators). Phenytoin often causes a
decline in plasma carbamazepine levels if these two
drugs are given concomitantly.
Ethotoin and mephenytoin are congeners of phenytoin
that are marketed as AEDs in the United States.
They are not widely used.
Side effects
The rapid IV administration of phenytoin can present a
hazard. Respiratory arrest, arrhythmias, and hypotension
have been reported.
Synthesis
Phenytoin, 5,5-diphenylimidazolidinedione (9.1.1) is synthesized in two different
ways. The first involves a rearrangement on the reaction of benzil with urea to form the desired
product (9.1.1) .

The second method involves the reaction of benzophenone with sodium cyanide in the
presence of ammonium carbonate, followed by the simultaneous cyclization of the resulting product (carboxyaminonitrile) and its rearrangement under the reaction conditions to
form phenytoin .
Drug interactions
Plasma phenytoin concentrations are increased in the
presence of chloramphenicol, disulfiram, and isoniazid,
since the latter drugs inhibit the hepatic metabolism of
phenytoin. A reduction in phenytoin dose can alleviate
the consequences of these drug–drug interactions.
Carcinogenicity
Phenytoin and its sodium salt are reasonably anticipated to be human carcinogens based on sufficient evidence from studies in experimental animals.
Environmental Fate
Routes and Pathways
Exposure is usually oral, but the intravenous route may be used
to treat status epilepticus.
Relevant Physicochemical Properties
Appearance: clear, colorless, or slightly yellow in solution
Solubility: ethyl alcohol
Metabolism
Phenytoin is hydroxylated in the liver to inactive
metabolites chiefly 5-(4-hydroxyphenyl)-5-
phenylhydantoin by an enzyme system which is
saturable. Phenytoin undergoes enterohepatic recycling
and is excreted in the urine, mainly as its hydroxylated
metabolite, in either free or conjugated form.
Solubility in water
practically insoluble in water. 1 g dissolves in about 75 ml of ethanol or 30 ml of acetone.
Purification Methods
Crystallise the hydantoin from EtOH. [Beilstein 24 III/IV 1748.]
Toxicity evaluation
Since metabolism of the drug is a saturable process, much of
the toxicity of phenytoin is thought to be due to increased
concentrations of the drug, especially of nonprotein-bound
drug. The free drug may cross the blood–brain barrier, and if
present in excess, could produce some of the adverse neurological
manifestations. Other toxicities may be related to folic
acid deficiency induced by phenytoin. Reactive intermediates
formed during metabolism of phenytoin may also be responsible
for some of the drug’s toxicity.
Toxics Screening Level
This oral
dose can be converted to an inhalation RfC using a weight of 70 kg person and
breathing 20 m3, resulting in a potential ITSL of 100 μg/m3 24-hour average.
Precautions
Phenytoin either should not be used or should be used
cautiously in patients with hypotension, severe bradycardia,
high-grade A-V block, severe heart failure, or
hypersensitivity to the drug.
Because of the increase in A-V transmission observed
with phenytoin administration, it should not be
given to patients with atrial flutter or atrial fibrillation.
Phenytoin will probably not restore normal sinus
rhythm and may dangerously accelerate the ventricular
rate.
References
[1] BOUCHER B A. Fosphenytoin: A Novel Phenytoin Prodrug[J]. Pharmacotherapy, 1996, 495. DOI:
10.1002/j.1875-9114.1996.tb02996.x[2] DR YOEL YAARI PHD Michael E S M, PHD Jonathan H P M. Phenytoin: Mechanisms of its anticonvulsant action[J]. Annals of Neurology, 1986, 20 2: 171-184. DOI:
10.1002/ana.410200202[3] P CALABRESI. An in vitro electrophysiological study on the effects of phenytoin, lamotrigine and gabapentin on striatal neurons[J]. British Journal of Pharmacology, 2009, 126 3: 689-696. DOI:
10.1038/sj.bjp.0702361[4] WAYNE J. BROUILLETTE. Bicyclic Hydantoins with a Bridgehead Nitrogen. Comparison of Anticonvulsant Activities with Binding to the Neuronal Voltage-Dependent Sodium Channel[J]. Journal of Medicinal Chemistry, 1994, 37 20: 3289-3293. DOI:
10.1021/jm00046a013