Description
Originally isolated from hypothalamic tissue, somatostatin is characterized as an inhibitor of growth hormone (GH) release.
The structure was determined in 1971. Subsequent investigations led to the recognition that somatostatin also was
released from the pancreas and has a role of inhibiting the secretion of both insulin and glucagon. A total of five
somatostatin receptor subtypes have been characterized and cloned (sst1 to sst5).
Subtype sst4 is associated with the
inhibition of insulin release, and an sst4-selective inhibitor has been reported. The somatostatin analogue SOM230
has exhibited selectivity for sst1, sst2, sst3, and sst5 in rats and effectively decreased plasma GH and insulin-like growth
factor-1 (IGF-1) levels by 75% without significant effects on insulin or glucagon. Another analogue, PT R3173, with
selectivity for recombinant human somatostatin receptor (hsst2, hsst4, hsst5) was substantially more effective in inhibiting
GH secretion compared to glucagon and insulin release in rats.
Uses
Somatostatin is a peptide hormone that regulates the endocrine system.
Indications
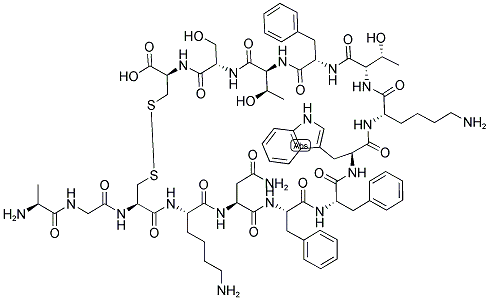
Somatostatin (51110-01-1) occurs primarily as a 14–amino acid peptide, although a 28–amino acid form also exists.As with the other hypothalamic peptides, it is formed by proteolytic cleavage of a larger precursor. Somatostatin, originally isolated from the hypothalamus, is also in many other locations, including the cerebral cortex, brainstem, spinal cord, gut, urinary system, and skin. Somatostatin inhibits the secretion of many substances in addition to growth hormone.
General Description
Somatostatin was discovered in the hypothalamus. It is elaboratedby the δ-cells of the pancreas and elsewhere in thebody. Somatostatin is an oligopeptide (14 amino acidresidues) and is referred to as somatotropin release–inhibitingfactor (SRIF).
Its primary action is inhibiting the release of GH from thepituitary gland. Somatostatin also suppresses the release ofboth insulin and glucagon. It causes a decrease in bothcAMP levels and adenylate cyclase activity. It also inhibitscalcium ion influx into the pituitary cells and suppressesglucose-induced pancreatic insulin secretion by activatingand deactivating potassium ion and calcium ion permeability,respectively. The chemistry, SARs, and potential clinicalapplications have been reviewed.
Mechanism of action
Somatostatin binds to 6 somatostatin receptor (SSTR) subtypes, which are G protein-coupled receptors (GPCRs) that inhibit adenylate cyclase after activation. It then inhibits intracellular cyclic adenosine monophosphate and Ca2+, while increasing outward potassium currents, ultimately reducing target tissue hormone secretion. Somatostatin can also achieve anti-tumor effects through anti-proliferation and cell inhibition.
Clinical Use
Somatostatin has a very brief half-life in serum and
is not useful clinically.An 8–amino acid analogue with 2
D-amino acids substituted for the naturally occurring
L-amino acids is more stable, and monthly injections of
a depot form of this analogue (octreotide, Sandostatin
LAR) have several uses. Long-acting octreotide is used
to treat acromegaly, as described earlier. It is also used
to counteract unpleasant effects caused by overproduction
of secreted bioactive substances produced by neuroendocrine
tumors, including hyperinsulinemia from
insulinomas and secretions from carcinoid tumors that
cause severe diarrhea. Octreotide may also control severe
diarrhea associated with AIDS that has not responded
to other treatments.
Side effects
Transient side effects, gastrointestinal discomfort
and decreased glucose tolerance, usually last only a few
weeks after initiation of therapy. The most significant
side effect associated with prolonged use of octreotide
is formation of gallstones resulting from reduced bile
flow.

 ;
 ;