
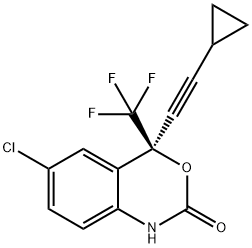
154598-52-4
| Name | Efavirenz |
| CAS | 154598-52-4 |
| EINECS(EC#) | 620-492-6 |
| Molecular Formula | C14H9ClF3NO2 |
| MDL Number | MFCD05662344 |
| Molecular Weight | 315.67 |
| MOL File | 154598-52-4.mol |
Synonyms
MDP-266
DMP 266
Stocrin
SUSTIVA
L-743726
EFAVIRNEZ
EFAVIRENZ
efavuirenz
Efavirenz-D5
Efavirenz&Int.
Efavirenz (200 mg)
(4S)-6-chloro-4-(2-cyclopropylethynyl)-4-(trifluoromethyl)-1H-3,1-benzoxazin-2-one
(S)-6-CHLORO-4-(CYCLOPROPYLETHYNYL)-4-(TRIFLUOROMETHYL)-1H-BENZO[D][1,3]OXAZIN-2(4H)-ONE
(S)-6-Chloro-4-(cyclopropylethynyl)-1,4-dihydro-4-(trifluoromethyl) 2H-3,1-benzoxazin-2-one
(4s)-6-chloro-4-(cyclopropylethynyl)-1,4-dihydro-4-(trifluoromethyl)-2h-3,1-benzoxazin-2-one
(4S)-6-Chloro-4-(cyclopropylethynyl)-4-(trifluoromethyl)-1,4-dihydro-(2H)-3,1-benzoxazin-2-one
(4S)-6-Chloro-4-(2-cyclopropylethynyl)-1,4-dihydro-4-(trifluoromethyl)-2H-3,1-benzoxazin-2-one
(4S)-6-chloro-4-(2-cyclopropylethynyl)-4-(trifluoroMethyl)-2,4-dihydro-1H-3,1-benzoxazin-2-one
2H-3,1-Benzoxazin-2-one, 6-chloro-4-(cyclopropylethynyl)-1,4-dihydro-4-(trifluoromethyl)-, (S)-
2H-3,1-Benzoxazin-2-one, 6-chloro-4-(cyclopropylethynyl)-1,4-dihydro-4-(trifluoromethyl)-, (4S)-
2H-3,1-Benzoxazin-2-one, 6-chloro-4-(2-cyclopropylethynyl)-1,4-dihydro-4-(trifluoroMethyl)-, (4S)-
Chemical Properties
| Appearance | White to Slightly Pink Crystalline Powder |
| Melting point | 139-141°C |
| alpha | D20 -84.7° (c = 0.005 g/ml in CH3Cl); D25 -94.1° (c = 0.300 in methanol) |
| Boiling point | 340.6±42.0 °C(Predicted) |
| density | 1.53±0.1 g/cm3(Predicted) |
| Fp | 2℃ |
| storage temp. | -20°C Freezer |
| solubility | DMSO: soluble15mg/mL, clear |
| form | powder or crystals |
| pka | 10.2(at 25℃) |
| color | white to beige |
| Optical Rotation | [α]/D -90 to -100°, c = 1 in methanol |
| Water Solubility | 8mg/L(temperature not stated) |
| λmax | 247nm(MeOH)(lit.) |
| Merck | 14,3521 |
| BCS Class | 4 |
| InChI | 1S/C14H9ClF3NO2/c15-9-3-4-11-10(7-9)13(14(16,17)18,21-12(20)19-11)6-5-8-1-2-8/h3-4,7-8H,1-2H2,(H,19,20)/t13-/m0/s1 |
| InChIKey | XPOQHMRABVBWPR-ZDUSSCGKSA-N |
| SMILES | ClC1=CC=C2C([C@@](C#CC3CC3)(C(F)(F)F)OC(N2)=O)=C1 |
| EPA Substance Registry System | 2H-3,1-Benzoxazin-2-one, 6-chloro-4-(2-cyclopropylethynyl)-1,4-dihydro-4-(trifluoromethyl)-, (4S)- (154598-52-4) |
Safety Data
| Hazard Codes | N |
| Risk Statements | |
| Safety Statements | |
| RIDADR | UN3082 - class 9 - PG 3 - DOT NA1993 - Environmentally hazardous substances, liquid, n.o.s. HI: all (not BR) |
| WGK Germany | 3 |
| RTECS | DM3440000 |
| HS Code | 2934990002 |
| Storage Class | 6.1C - Combustible acute toxic Cat.3 toxic compounds or compounds which causing chronic effects |
| Hazard Classifications | Acute Tox. 4 Oral Aquatic Acute 1 Aquatic Chronic 1 Repr. 1B |
| Hazardous Substances Data | 154598-52-4(Hazardous Substances Data) |
Hazard Information
Chemical Properties
White to Slightly Pink Crystalline Powder
Usage
A nonnucleoside HIV-1 reverse transcriptase inhibitor. Antiviral
Usage
antiviral;reverse transcriptase inhibitor
Usage
For use in combination treatment of HIV infection (AIDS)
Description
Efavirenz D5 was launched as Sustiva in the US for the treatment of infection by HIV, the virus causing AIDS, in combination with other anti-retroviral agents.
Efavirenz D5 is a non-nucleoside reverse transcriptase inhibitor (NNRTI) belonging to the 3,1-benzoxazin-2-one chemical class. It is the third non-nucleoside reverse transcriptase inhibitor to have been launched to date, after Nevirapine (1996) and Delavirdine (1997), increasing the arsenal of anti-HIV drugs for treating infected patients in dual or triple combination with nucleoside or other non-nucleoside RTIs, or protease inhibitors.
Efavirenz D5 can be obtained by two related ways of six steps from 4-chloroaniline ; one of them is based on asymmetric synthesis by enantioselective addition of an acetylide to a trifluoroacetophenone. The anti-HIV activity of Efavirenz D5 was demonstrated against most wild-type and clinical strains of HIV-1, including those with the most frequently observed mutations. Efavirenz D5 has a better pharmacokinetic profile when compared with the preceding drugs of this class ; in particular, in a long-term experiment conducted in cynomolgus monkeys, Efavirenz D5 was shown to easily cross the blood brain barrier leading to an increase of the antiviral concentration in cerebrospinal fluid.
Efavirenz D5 is a non-nucleoside reverse transcriptase inhibitor (NNRTI) belonging to the 3,1-benzoxazin-2-one chemical class. It is the third non-nucleoside reverse transcriptase inhibitor to have been launched to date, after Nevirapine (1996) and Delavirdine (1997), increasing the arsenal of anti-HIV drugs for treating infected patients in dual or triple combination with nucleoside or other non-nucleoside RTIs, or protease inhibitors.
Efavirenz D5 can be obtained by two related ways of six steps from 4-chloroaniline ; one of them is based on asymmetric synthesis by enantioselective addition of an acetylide to a trifluoroacetophenone. The anti-HIV activity of Efavirenz D5 was demonstrated against most wild-type and clinical strains of HIV-1, including those with the most frequently observed mutations. Efavirenz D5 has a better pharmacokinetic profile when compared with the preceding drugs of this class ; in particular, in a long-term experiment conducted in cynomolgus monkeys, Efavirenz D5 was shown to easily cross the blood brain barrier leading to an increase of the antiviral concentration in cerebrospinal fluid.
Originator
Merck & Co. (US)
Uses
antiviral;reverse transcriptase inhibitor
Uses
Efavirenz D5 is a nonnucleoside HIV-1 reverse transcriptase inhibitor. Antiviral
Uses
For use in combination treatment of HIV infection (AIDS)
Definition
ChEBI: 1,4-Dihydro-2H-3,1-benzoxazin-2-one substituted at the 4 position by cyclopropylethynyl and trifluoromethyl groups (S configuration) and at the 6 position by chlorine. A non-nucleoside reverse transcriptase inhibitor wit
activity against HIV, it is used with other antiretrovirals for combination therapy of HIV infection.
Indications
Efavirenz (Sustiva) is approved for the therapy of HIV
infection of adults and children and is also used for postexposure
prophylaxis. It is the only NNRTI approved
for once-daily dosing. Rash, although rarely severe, is a
common adverse effect of efavirenz. Elevated liver enzymes
and serum cholesterol also may occur. Central
nervous system (CNS) effects in approximately half of
patients may include dizziness, headache, insomnia,
drowsiness, euphoria, agitation, impaired cognition,
nightmares, vivid dreams, and hallucinations. These effects
often subside after several weeks to months of
therapy.
Manufacturing Process
(-)-6-Chloro-4-cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H-3,1-
benzoxazin-2-one and (+) 6-Chloro-4-cyclopropylethynyl-4-trifluoromethyl-
1,4-dihydro-2H-3,1-benzoxazin-2-one
The above products can be produced in the next steps:
Step A: 2-(2-Amino-5-chlorophenyl)-4-cyclopropyl-1,1,1-trifluoro-3-butyn-2- ol.
A solution, was prepared from 23 g of cyclopropylacetylene (0.348 mol) in 250 mL of THF by dropwise addition of 116 mL of a 3.0 M solution of ethylmagnesium bromide in ether (0.348 mol) over 1 h. This solution was maintained at 0°C for 1 h, then at 40°C for 3 h. To this solution, recooled to 0°C, 15.56 g of 1-(2-amino-5-chlorophenyl)-2,2,2-trifluoromethylethanone (0.0696 mol), was added as a solid, portionwise over 5 min. The reaction mixture was allowed to stir at 0°C for 1.5 hours. The reaction was quenched at 0°C by dropwise addition of 700 mL of saturated aqueous ammonium chloride solution. The mixture was extracted with 2 times 400 mL portions of ethyl acetate, the combined organic phases were washed with brine and dried over MgSO4. Removal of the drying agent and solvents left a yellow solid. This material was recrystallized from boiling hexanes (100 mL final volume) to afford 14.67 g of 2-(2-amino-5-chlorophenyl)-4-cyclopropyl-1,1,1-trifluoro-3- butyn-2-ol. A second crop (2.1 g) was obtained from concentrating the mother liquors. M.p.: 153°-154°C.
Step B: ()-6-Chloro-4-cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H- 3,1-benzoxazin-2-one.
A solution of 2-(2-amino-5-chlorophenyl)-4-cyclopropyl-1,1,1-trifluoro-3- butyn-2-ol (15.00 g, 0.0518 mol) and 41.98 g (0.259 mol) of 1,1'- carbonyldiimidazole in 250 mL of dry THF was stirred under argon at 55°C for 24 hours. The solvent was removed on a rotary evaporator and the residue was partitioned between 500 mL of ethyl acetate and 400 mL of water. The layers were separated and the aqueous phase was extracted once more with ethyl acetate. The combined ethyl acetate extracts were washed with 2 times 200 mL of 2% aqueous HCl, saturated aqueous NaHCO3, and brine. Drying over MgSO4, filtration, and removal of the solvent in vacuo provided 16.42 g of the title compound as a solid. Recrystallization from ethyl acetate/hexane afforded 12.97 g of analytically pure ()-6-chloro-4-cyclopropylethynyl-4- trifluoromethyl-1,4-dihydro-2H-3,1-benzoxazin-2-one as a white crystals. Melting point: 178°-180°C.
Step C: 6-Chloro-1-(1S)-camphanoyl-4-cyclopropylethynyl-4-trifluoromethyl- 1,4-dihydro-2H-3,1-benzoxazin-2-one.
To a solution containing (+)-6-chloro-4-cyclopropylethynyl-4-trifluoromethyl- 1,4-dihydro-2H-3,1-benzoxazin-2-one (12.97 g, 0.041 mol), 4- dimethylaminopyridine (1.02 g, 0.0083 mol), and (-)-camphanic acid chloride (14.22 g, 0.06556 mol) in 350 mL of dry dichloromethane, stirred under argon in an ice bath, was added triethylamine (22.84 mL, 0.164 mol). The cooling bath was removed and the reaction was allowed to proceed at room temperature. After 75 min. the reaction was judged complete by thin layer chromatography (SiO2, 4% EtOAc in CHCl3), and the solution was diluted with 500 mL of CHCl3 then washed with 10% citric acid (2X), water (1X), and brine (1X). Drying (MgSO4), filtration, and removal of the solvent in vacuo left a colorless foam. This material was triturated with 200 mL of boiling hexane. On cooling to room temperature the desired diastereomeric camphanate imide precipitated. The solid was collected on a frit, washed with a little cold hexanes and dried in vacuo to give 7.79 g of 6-chloro-1-(1S)-camphanoyl-4- cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H-3,1-benzoxazin-2-one as white crystals. Melting point: 164°-165°C. HPLC purity: 99.2% γ 254 nm.
Step D: (-)-6-Chloro-4-cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H- 3,1-benzoxazin-2-one.
6-Chloro-1-(1S)-camphanoyl-4-cyclopropylethynyl-4-trifluoromethyl-1,2- dihydro-4(H)-3,1-benzoxazin-2-one(7.50 g, 0.01512 mol) was dissolved in 150 mL of n-butanol at 60°C under an atmosphere of argon. To this solution was added 10 mL of 1 N HCl. This solution was maintained at 60°C for 72 h. The mixture was neutralized with aqueous NaHCO3 and the n-butanol was removed in vacuo. The residue was dissolved in 150 mL of THF and treated with 50 mL of 2 N LiOH for 3 h at room temperature. This mixture was diluted with ethyl acetate and washed with two portions of water and one of brine. Drying (MgSO4), filtration and removal of the solvent in vacuo gave a white solid. This material was recrystallized from hot hexane to give 3.43 g of (-)-6- chloro-4-cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H-3,1-benzoxazin- 2-one as white crystals, melting point 131°-132°C, [α]D20 = - 84.7° (CHCl3, c=0.005 g /mL).Step E: (+)-6-Chloro-4-cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H- 3,1-benzoxazin-2-one.
The mother liquors from Step C above were purified by column chromatography on silica gel using 10% ethyl acetate in hexanes as eluant. The pure, undesired diastereomer (a colorless foam) was hydroylzed according to Step D. The enantiomeric benzoxazinone, (+)-6-chloro-4- cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H-3,1-benzoxazin-2-one, was obtained as white crystals. Melting point 131°-132°C; [α]D20 =+84.4° (CHCl3, c=0.005 g/mL).
The above products can be produced in the next steps:
Step A: 2-(2-Amino-5-chlorophenyl)-4-cyclopropyl-1,1,1-trifluoro-3-butyn-2- ol.
A solution, was prepared from 23 g of cyclopropylacetylene (0.348 mol) in 250 mL of THF by dropwise addition of 116 mL of a 3.0 M solution of ethylmagnesium bromide in ether (0.348 mol) over 1 h. This solution was maintained at 0°C for 1 h, then at 40°C for 3 h. To this solution, recooled to 0°C, 15.56 g of 1-(2-amino-5-chlorophenyl)-2,2,2-trifluoromethylethanone (0.0696 mol), was added as a solid, portionwise over 5 min. The reaction mixture was allowed to stir at 0°C for 1.5 hours. The reaction was quenched at 0°C by dropwise addition of 700 mL of saturated aqueous ammonium chloride solution. The mixture was extracted with 2 times 400 mL portions of ethyl acetate, the combined organic phases were washed with brine and dried over MgSO4. Removal of the drying agent and solvents left a yellow solid. This material was recrystallized from boiling hexanes (100 mL final volume) to afford 14.67 g of 2-(2-amino-5-chlorophenyl)-4-cyclopropyl-1,1,1-trifluoro-3- butyn-2-ol. A second crop (2.1 g) was obtained from concentrating the mother liquors. M.p.: 153°-154°C.
Step B: ()-6-Chloro-4-cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H- 3,1-benzoxazin-2-one.
A solution of 2-(2-amino-5-chlorophenyl)-4-cyclopropyl-1,1,1-trifluoro-3- butyn-2-ol (15.00 g, 0.0518 mol) and 41.98 g (0.259 mol) of 1,1'- carbonyldiimidazole in 250 mL of dry THF was stirred under argon at 55°C for 24 hours. The solvent was removed on a rotary evaporator and the residue was partitioned between 500 mL of ethyl acetate and 400 mL of water. The layers were separated and the aqueous phase was extracted once more with ethyl acetate. The combined ethyl acetate extracts were washed with 2 times 200 mL of 2% aqueous HCl, saturated aqueous NaHCO3, and brine. Drying over MgSO4, filtration, and removal of the solvent in vacuo provided 16.42 g of the title compound as a solid. Recrystallization from ethyl acetate/hexane afforded 12.97 g of analytically pure ()-6-chloro-4-cyclopropylethynyl-4- trifluoromethyl-1,4-dihydro-2H-3,1-benzoxazin-2-one as a white crystals. Melting point: 178°-180°C.
Step C: 6-Chloro-1-(1S)-camphanoyl-4-cyclopropylethynyl-4-trifluoromethyl- 1,4-dihydro-2H-3,1-benzoxazin-2-one.
To a solution containing (+)-6-chloro-4-cyclopropylethynyl-4-trifluoromethyl- 1,4-dihydro-2H-3,1-benzoxazin-2-one (12.97 g, 0.041 mol), 4- dimethylaminopyridine (1.02 g, 0.0083 mol), and (-)-camphanic acid chloride (14.22 g, 0.06556 mol) in 350 mL of dry dichloromethane, stirred under argon in an ice bath, was added triethylamine (22.84 mL, 0.164 mol). The cooling bath was removed and the reaction was allowed to proceed at room temperature. After 75 min. the reaction was judged complete by thin layer chromatography (SiO2, 4% EtOAc in CHCl3), and the solution was diluted with 500 mL of CHCl3 then washed with 10% citric acid (2X), water (1X), and brine (1X). Drying (MgSO4), filtration, and removal of the solvent in vacuo left a colorless foam. This material was triturated with 200 mL of boiling hexane. On cooling to room temperature the desired diastereomeric camphanate imide precipitated. The solid was collected on a frit, washed with a little cold hexanes and dried in vacuo to give 7.79 g of 6-chloro-1-(1S)-camphanoyl-4- cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H-3,1-benzoxazin-2-one as white crystals. Melting point: 164°-165°C. HPLC purity: 99.2% γ 254 nm.
Step D: (-)-6-Chloro-4-cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H- 3,1-benzoxazin-2-one.
6-Chloro-1-(1S)-camphanoyl-4-cyclopropylethynyl-4-trifluoromethyl-1,2- dihydro-4(H)-3,1-benzoxazin-2-one(7.50 g, 0.01512 mol) was dissolved in 150 mL of n-butanol at 60°C under an atmosphere of argon. To this solution was added 10 mL of 1 N HCl. This solution was maintained at 60°C for 72 h. The mixture was neutralized with aqueous NaHCO3 and the n-butanol was removed in vacuo. The residue was dissolved in 150 mL of THF and treated with 50 mL of 2 N LiOH for 3 h at room temperature. This mixture was diluted with ethyl acetate and washed with two portions of water and one of brine. Drying (MgSO4), filtration and removal of the solvent in vacuo gave a white solid. This material was recrystallized from hot hexane to give 3.43 g of (-)-6- chloro-4-cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H-3,1-benzoxazin- 2-one as white crystals, melting point 131°-132°C, [α]D20 = - 84.7° (CHCl3, c=0.005 g /mL).Step E: (+)-6-Chloro-4-cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H- 3,1-benzoxazin-2-one.
The mother liquors from Step C above were purified by column chromatography on silica gel using 10% ethyl acetate in hexanes as eluant. The pure, undesired diastereomer (a colorless foam) was hydroylzed according to Step D. The enantiomeric benzoxazinone, (+)-6-chloro-4- cyclopropylethynyl-4-trifluoromethyl-1,4-dihydro-2H-3,1-benzoxazin-2-one, was obtained as white crystals. Melting point 131°-132°C; [α]D20 =+84.4° (CHCl3, c=0.005 g/mL).
Brand name
Sustiva (Bristol-Myers Squibb).
Therapeutic Function
Antiviral
Acquired resistance
One or more single-codon substitutions in the HIV reverse
transcriptase genome at positions 100, 103, 106, 108, 181,
188, 190 and 225 confer reduced susceptibility. Many, but
not all, of these point mutations confer reduced susceptibility
to other non-nucleoside reverse transcriptase inhibitors.
General Description
Efavirenz D5 (Sustiva)84 is also mandated for use with at leasttwo other antiretroviral agents. The compound is morethan 99% protein bound, and CSF concentrations exceedthe free fraction in the serum. Metabolism occurs in theliver. The half-life of a single dose of Efavirenz D5 is 52 to 76hours, and 40 to 55 after multiple doses (the drug inducesits own metabolism). Peak concentration is achieved in 3to 8 hours. Elimination is 14% to 34% in urine (as metabolites)and 16% to 41% in feces (primarily as Efavirenz D5).The oral dosage form is supplied as a capsule.
Pharmaceutical Applications
Efavirenz D5 is a synthetic heterocyclic compound formulated for oral administration.
Biochem/physiol Actions
Efavirenz is a nonnucleoside reverse transcriptase inhibitor (NNRTI). It is an anti-HIV drug, commonly used in combination therapy for AIDs treatment. It is part of highly active antiretroviral therapy (HAART) for the treatment of a human immunodeficiency virus (HIV) type 1.
Pharmacokinetics
Oral absorption: Not known/available
Cmax 600 mg oral once daily: c. 4.07 mg/L
Cmin 600 mg oral once daily: c. 1.77 mg/L
Plasma half-life: c. 45 h
Volume of distribution: c. 2.4 L/kg
Plasma protein binding: >99%
Absorption and distribution
Bioavailability following a standard high-fat meal was increased by an average of 50%, but was unaffected by a standard meal. Distribution into body tissues and fluids has not been fully characterized. It penetrates moderately well into the CNS. The semen:plasma ratio is 0.09 (0.03–0.43). The mean concentration in breast milk is 3.51 mg/L; significant linear correlations have been found between maternal plasma and breast milk.
Metabolism and excretion
It is metabolized by cytochrome P450 systems to hydroxylated intermediates and excreted after subsequent glucuronidation. Metabolites are not active against HIV.
It is excreted principally in the feces, both as metabolites and unchanged drug. Up to 34% is recovered in the urine, <1% as unchanged drug. Given this, the impact of renal impairment on efavirenz is likely to be minimal. Caution is recommended in patients with mild–moderate liver disease; it is contraindicated in patients with severe hepatic impairment.
Dose adjustment is unnecessary when it is co-administered with HIV protease inhibitors or rifampicin (rifampin).
Cmax 600 mg oral once daily: c. 4.07 mg/L
Cmin 600 mg oral once daily: c. 1.77 mg/L
Plasma half-life: c. 45 h
Volume of distribution: c. 2.4 L/kg
Plasma protein binding: >99%
Absorption and distribution
Bioavailability following a standard high-fat meal was increased by an average of 50%, but was unaffected by a standard meal. Distribution into body tissues and fluids has not been fully characterized. It penetrates moderately well into the CNS. The semen:plasma ratio is 0.09 (0.03–0.43). The mean concentration in breast milk is 3.51 mg/L; significant linear correlations have been found between maternal plasma and breast milk.
Metabolism and excretion
It is metabolized by cytochrome P450 systems to hydroxylated intermediates and excreted after subsequent glucuronidation. Metabolites are not active against HIV.
It is excreted principally in the feces, both as metabolites and unchanged drug. Up to 34% is recovered in the urine, <1% as unchanged drug. Given this, the impact of renal impairment on efavirenz is likely to be minimal. Caution is recommended in patients with mild–moderate liver disease; it is contraindicated in patients with severe hepatic impairment.
Dose adjustment is unnecessary when it is co-administered with HIV protease inhibitors or rifampicin (rifampin).
Pharmacology
Efavirenz interacts with many drugs via the cytochrome
P450 pathways. It induces and is metabolized
by CYP3A4 and inhibits CYP2C9 and CYP2C19. It
should not be given with cisapride, ergot alkaloids, midazolam,
or triazolam because of the potential for lifethreatening
reactions. Efavirenz has the potential to
decrease blood levels of methadone, rifabutin, ketoconazole,
and itraconazole. It may inhibit the metabolism
of drugs such as alosetron, diazepam, ethinyl estradiol,
imipramine, losartan, omeprazole, warfarin,
tolbutamide, and topiramate. Efavirenz interacts with
cytochrome P450 inducers and substrates (e.g., phenytoin,
phenobarbital) in a complex manner; blood levels
and side effects should be closely monitored. Patients
taking efavirenz should avoid herbal preparations containing
St. John’s wort because the herb induces
CYP3A4 and may cause drug failure or viral resistance.
Saquinavir should not be used as the sole protease inhibitor
in a regimen containing efavirenz.
Clinical Use
Treatment of HIV-1 infection in adults and children (in combination with
other antiretroviral drugs)
Side effects
The most common (>5%, moderate–severe) adverse effects associated with Efavirenz D5 therapy are rash, dizziness, nausea, headache, fatigue, insomnia and vomiting. Rash occurs in up to 26% of patients, mostly in the first 2 weeks of therapy. It usually resolves within 1 month, but is sufficiently severe to limit treatment in a few cases.
Dizziness, insomnia, somnolence, impaired concentration, abnormal dreaming and other CNS disturbances have been reported in around 52% of clinical trial participants, with events of moderate to severe intensity occurring in about 3% of patients. Rare (0.2% of patients) episodes of severe delusional or inappropriate behavior and severe acute depression have also been reported. The symptoms commonly begin in the first 2 weeks of treatment but often resolve or substantially improve within a month.
Elevations in serum hepatic transaminase to levels more than five times the upper limit of normal are observed in about 3% of patients and 8% of those co-infected with viral hepatitis B or C.
Dizziness, insomnia, somnolence, impaired concentration, abnormal dreaming and other CNS disturbances have been reported in around 52% of clinical trial participants, with events of moderate to severe intensity occurring in about 3% of patients. Rare (0.2% of patients) episodes of severe delusional or inappropriate behavior and severe acute depression have also been reported. The symptoms commonly begin in the first 2 weeks of treatment but often resolve or substantially improve within a month.
Elevations in serum hepatic transaminase to levels more than five times the upper limit of normal are observed in about 3% of patients and 8% of those co-infected with viral hepatitis B or C.
Drug interactions
Potentially hazardous interactions with other drugs
Antibacterials: concentration of rifabutin reduced.
Anticoagulants: possibly affects concentration of coumarins.
Antidepressants: concentration reduced by St John’s wort - avoid.
Antifungals: itraconazole, posaconazole and voriconazole concentration reduced; voriconazole increases efavirenz concentration - reduce dose of efavirenz by 50% and increase dose of voriconazole to 400 mg twice daily; possibly reduces caspofungin concentration - may possibly need to increase caspofungin dose.
Antimalarials: concentration of artemether with lumefantrine reduced.
Antipsychotics: possibly increased risk of ventricular arrhythmias with pimozide - avoid; possibly reduces aripiprazole concentration - increase aripiprazole dose
Antivirals: concentration of atazanavir and boceprevir reduced - avoid; saquinavir concentration significantly reduced; concentration of daclatasvir, darunavir, dolutegravir, indinavir, lopinavir, telaprevir and possibly etravirine and maraviroc reduced - adjust daclatasvir, darunavir, dolutegravir, lopinavir, maraviroc and telaprevir dose, avoid with etravirine; concentration reduced by nevirapine; monitor LFTs when used in combination with ritonavir.
Anxiolytics and hypnotics: risk of prolonged sedation with midazolam - avoid.
Atovaquone: concentration of atovaquone reduced - avoid.
Ciclosporin: concentration of ciclosporin possibly reduced.
Cytotoxics: concentration of bosutinib possibly reduced - avoid
Ergot alkaloids: risk of ergotism - avoid.
Grapefruit juice: concentration possiblyincreased.
Guanfacine: concentration of guanfacine possibly reduced, increase dose of guanfacine
Oestrogens and progestogens: possibly reduced contraceptive effect.
Orlistat: absorption possibly reduced by orlistat.
Tacrolimus: possibly affects tacrolimus concentration.
Ulipristal: possibly reduced contraceptive effect.
Antibacterials: concentration of rifabutin reduced.
Anticoagulants: possibly affects concentration of coumarins.
Antidepressants: concentration reduced by St John’s wort - avoid.
Antifungals: itraconazole, posaconazole and voriconazole concentration reduced; voriconazole increases efavirenz concentration - reduce dose of efavirenz by 50% and increase dose of voriconazole to 400 mg twice daily; possibly reduces caspofungin concentration - may possibly need to increase caspofungin dose.
Antimalarials: concentration of artemether with lumefantrine reduced.
Antipsychotics: possibly increased risk of ventricular arrhythmias with pimozide - avoid; possibly reduces aripiprazole concentration - increase aripiprazole dose
Antivirals: concentration of atazanavir and boceprevir reduced - avoid; saquinavir concentration significantly reduced; concentration of daclatasvir, darunavir, dolutegravir, indinavir, lopinavir, telaprevir and possibly etravirine and maraviroc reduced - adjust daclatasvir, darunavir, dolutegravir, lopinavir, maraviroc and telaprevir dose, avoid with etravirine; concentration reduced by nevirapine; monitor LFTs when used in combination with ritonavir.
Anxiolytics and hypnotics: risk of prolonged sedation with midazolam - avoid.
Atovaquone: concentration of atovaquone reduced - avoid.
Ciclosporin: concentration of ciclosporin possibly reduced.
Cytotoxics: concentration of bosutinib possibly reduced - avoid
Ergot alkaloids: risk of ergotism - avoid.
Grapefruit juice: concentration possiblyincreased.
Guanfacine: concentration of guanfacine possibly reduced, increase dose of guanfacine
Oestrogens and progestogens: possibly reduced contraceptive effect.
Orlistat: absorption possibly reduced by orlistat.
Tacrolimus: possibly affects tacrolimus concentration.
Ulipristal: possibly reduced contraceptive effect.
Metabolism
Studies in humans and in vitro studies using human
liver microsomes have demonstrated that efavirenz
is principally metabolised by the cytochrome P450
system to hydroxylated metabolites with subsequent
glucuronidation of these hydroxylated metabolites. These
metabolites are essentially inactive against HIV-1. The
in vitro studies suggest that CYP3A4 and CYP2B6 are
the major isozymes responsible for efavirenz metabolism
and that it inhibited P450 isozymes 2C9, 2C19, and 3A4.
In in vitro studies efavirenz did not inhibit CYP2E1 and
inhibited CYP2D6 and CYP1A2 only at concentrations
well above those achieved clinically
Approximately 14-34% of a radiolabelled dose of efavirenz was recovered in the urine.
Approximately 14-34% of a radiolabelled dose of efavirenz was recovered in the urine.
Questions And Answer
-
Overview
Efavirenz[brand names Sustiva® and Stocrin®] is a kind of non-nucleoside reverse transcriptase inhibitor(NNRTI) and can be used as part of highly active antiretroviral therapy(HAART) for the treatment of a human immunodeficiency virus(HIV) type 1[1,2]. For HIV infection that has not previously been treated, efavirenz and lamivudine in combination with zidovudine or tenofovir is the preferred NNRTI-based regimen[1, 2]. Efavirenz can also be used in combination with other antiretroviral agents as part of an expanded postexposure prophylaxis regimen to prevent HIV transmission for those exposed to materials associated with a high risk for HIV transmission[1].
Efavirenz is one of the most commonly prescribed antiretroviral medications in the world. Several large randomized, controlled trials[RCTs] have demonstrated the superior ability of efavirenz to suppress the HIV virus when used as part of a 3-drug cocktail[2]. The introduction of Atripla in 2006 combined efavirenz and two other agents into a single pill, once-daily formulation. This formulation was more convenient and better tolerated than alternatives, and thus resulted in improved adherence to antiretroviral medications[3]. However, neuropsychiatric side effects associated with efavirenz have been reported to occur in 40–50% of patients and represent one of the limiting factors of this regimen[4].
Chemically it is described as[S]-6-chloro-4-[cyclopropylethynyl]-1,4-dihydro-4-(trifluoromethyl]-2H-3,1-benzoxazin-2-one. It has the empirical formula C14H9ClF3NO2, and its structural formula is presented in Figure 1[5].
Figure 1 The chemical structure of Efavirenz; -
Pharmacological aspects
Efavirenz D5 can be taken with or without food, but if taken with fatty food, its bioavailability and toxicity may increase. The oral solution has lower bioavailability than tablets or capsules. Efavirenz D5 is highly bound to human plasma proteins(approximately 99.7%), predominantly albumin[7]. It is principally metabolized by the cytochrome P450(CYP) system to hydroxylated metabolites with subsequent glucuronidation. These metabolites are essentially inactive against HIV-1. Efavirenz D5 drug has been shown to induce CYP enzymes, resulting in the induction of its own metabolism. Multiple doses of 200–400 mg per day for 10 days resulted in a lower-than predicted extent of accumulation(22%–42% lower) and a shorter terminal half-life of 40–55 hr(single-dose half life of 52–76 hr)6,7.
Drug interaction studies, through in vivo and in vitro tests, demonstrated that EFV is able to induce or inhibit the CYP isoenzymes. Efavirenz D5 has been shown in vivo to cause hepatic enzyme induction, thus increasing the biotransformation of some drugs metabolized by CYP3A(human gene of CYP, family 3, subfamily A), including auto-induction of its own metabolism. The inducing effect on CYP3A is expected to be similar for Efavirenz D5 doses of 200–600 mg. In vitro, the 2C9, 2C19, and 3A4 isoenzymes were inhibited by Efavirenz D5. Co-administration of efavirenz with drugs primarily metabolized by 2C9, 2C19, and 3A4 iso-zymes may result in altered plasma concentrations of the co-administered drug. Drugs that induce CYP3A activity would be expected to increase the clearance of Efavirenz D5, resulting in lowered plasma concentrations[5, 7,9,10]. ; -
Indications and action
Efavirenz is used in combination with other antiretroviral agents for the treatment of human immunodeficiency virus type 1(HIV-1) infection in adults and in pediatric patients at least 3 months old and weighing at least 3.5 kg. Efavirenz takes effect through inhibiting the activity of viral RNA-directed DNA polymerase(i.e., reverse transcriptase)[1, 11]. Antiviral activity of efavirenz is largely dependent on intracellular conversion to the active triphosphorylated form[1]. The rate of efavirenz phosphorylation varies, depending on the specific targeted cell type. It is generally proposed that inhibition of reverse transcriptase interferes with the generation of DNA copies of viral RNA, thus inhibiting the synthesis of new virions[1]. Intracellular enzymes subsequently eliminate the HIV particle that previously had been uncoated, and left unprotected, during entry into the host cell. Thus, reverse transcriptase inhibitors are virustatic and do not eliminate HIV from the body[1]. Even though human DNA polymerase is less susceptible to the pharmacologic effects of triphosphorylated efavirenz, this action may nevertheless account for some of the drug's toxicity. Efavirenz is an NNRTI of HIV-1, and its activity is mediated predominantly by noncompetitive inhibition of HIV-1 reverse transcriptase. HIV-2 reverse transcriptase is not inhibited by Efavirenz[12,13]. ; -
Drug resistance
Despite the good antiretroviral activity of efavirenz in vitro, repeated passage of HIV-1 in the presence of drug leads to a rapid selection of drug-resistant HIV-1 strains. A single mutation in the HIV-1 genome can increase the 50% inhibitory concentration(IC50) by up to 100-fold[14]. Clinical studies confirmed that resistant viruses also rapidly emerge in vivo, when efavirenz is used in the context of persistent viral replication[15]. The K103N mutation is most frequently the first resistance mutation to be selected[16,17]. However, the majority of patients go on to develop additional mutations, most commonly L100I, V106M, V108I, Y181C/I, Y188L, G190A/S and P225H[16,17] Although the Y181C mutation only reduces efavirenz susceptibility approximately twofold, efavirenz is often ineffective because of the fact that most patients failing a NNRTI-containing regimen harbour multiple different NNRTI-resistance mutations that are not detectable by standard genotyping. Double mutants are associated with higher levels of resistance to efavirenz. Joly et al[17]. Observed that, after switching to a non-NNRTI-containing regimen because of virological failure, NNRTI resistance mutations persist in two-thirds of the patients after 1 year. Thus, NNRTI mutations do not decrease replicative capacity, and, therefore, there is apparently no benefit in continuing NNRTI therapy once resistance has emerged. ; -
Adverse reactions
Efavirenz administration has been frequently associated with the manifestation of neuropsychiatric disorders including dizziness, confusion, lethargy, impaired concentration, amnesia, hallucinations, abnormal dreams, and insomnia[18, 19]. Anxiety, depression, and suicide have also been reported[20, 21]. Animal studies also confirm that Efavirenz affects anxiety-related behavior and cognitive performance[22,23].
Symptoms commonly appear in the first week of treatment[24-26], and most reports indicate that they usually disappear or reduce in severity after several weeks[21,24]. However, in a cross-sectional study of patients treated with Efavirenz, the psychiatric effects remained for up to 200 days, with a reduction in symptoms after this period[27]. A prospective study showed that neuropsychiatric symptoms occurred in the first 2 weeks of treatment but that those patients who continued to take Efavirenz showed an improvement in symptoms and were able to tolerate continued treatment[28]. Another study demonstrated that neuropsychiatric disorders might persist in patients chronically treated with Efavirenz[29]. Adverse effects and interactions of Efavirenz can affect the CNS. ; -
Precaution
The following tips should be concerned[30]:
You should not use efavirenz if you are allergic to it. The patients should consult his/her doctor if he/she has ever had liver disease(including hepatitis B or C), a seizure, mental illness or psychosis, heart disease or if he/she has alcoholism or injection drug administration history.
Since efavirenz can harm the unborn baby or cause birth defects, pregnant should be disabled. Use 2 forms of birth control, including a barrier form(condom, cervical cap, contraceptive sponge, or diaphragm with spermicide gel) to prevent pregnancy while you are using efavirenz and for at least 12 weeks after your last dose. Tell your doctor if you become pregnant during treatment. It should not be noted that hormonal contraception(birth control pills, injections, implants, skin patches, and vaginal rings) might fail in preventing pregnancy while you are taking efavirenz.
Women with HIV or AIDS should not breast-feed a baby. Even if your baby is born without HIV, the virus may be passed to the baby in your breast milk. ; -
References
- https://www.drugbank.ca/drugs/DB00625
- Gallant JE, DeJesus E, Arribas JR, Arribas JR, et al. Tenofovir DF, emtricitabine, and efavirenz vs. zidovudine, lamivudine, and efavirenz for HIV. N Engl J Med. 2006;354(3]:251–60.
- Ena J, Pasquau F. Once-a-day highly active antiretroviral therapy: a systematic review. Clin Infect Dis. 2003;36(9]:1186–90.
- Vrouenraets SM, Wit FW, van Tongeren J, et al. Efavirenz: a review. Expert Opin Pharmacother. 2007;8(6]:851–71.
- Efavirenz.[2009]. Sustiva. Rhodes, Greece: Cerner Multum.
- Date, H. L., & Fisher, M.[2009]. HIV infection. In R. Walker and C. Whittlesea[eds.], Clinical Pharmacy and Therapeutics, 4th ed. London: Churchill Livingstone Elsevier, 568–598
- Wande, A. N.[1994]. Handbook of Pharmaceutical excipients, 2th ed. Washington, DC: American Pharmaceutical Association.
- Skidmore-Roth, L.[2009]. Mosby’s Drug Guide of Nurses, 8th ed. St. Louis, MO: Mosby Elsevier, 346 pp.
- Almond, L. M., Hoggard, P. G., Edirisinghe, D. E., Khoo, S. H., & Back, D. J.[2005]. Intracellular and plasma pharmacokinetics of efavirenz in HIV-infected individuals. Journal of Antimicrobial Chemotherapy, 56, 738–744.
- Liu, P., Foster, G., LaBadie, R. R., Gutierrez, M. J., & Sharma, A.[2005]. Pharmacokinetic interaction between voriconazole and efavirenz at steady state in healthy subjects. Clinical Pharmacology & Therapeutics, 77, 40.
- https://www.rxlist.com/sustiva-drug.htm#indications
- Clercq, E.[2001]. Antiviral drugs: Current state of the art. Journal of Clinical Virology, 22, 73–89.
- Langmann, P., Schirmer,D., Vath, T., Zilly,M., &Klinker, H.[2001]. High-performance liquid chromatographic method for the determination of HIV-1 non-nucleoside reverse transcriptase inhibitor efavirenz in plasma of patients during highly active antiretroviral therapy. Journal of Chromatography. B, Biomedical Sciences and Applications, 755, 151–156.
- YOUNG SD, BRITCHER SF, TRAN LO et al.: L-743, 726(DMP-266]: a novel, highly potent nonnucleoside inhibitor of the human immunodeficiency virus type 1 reverse transcriptase. Antimicrob. Agents Chemother. (1995] 39(12]:2602-2605.
- DEEKS SG: International perspectives on antiretroviral resistance. Nonnucleoside reverse transcriptase inhibitor resistance. J. Acquir. Immune Defic. Syndr.[2001] 26[Suppl. 1]: S25-S33.
- BACHELER LT, ANTON ED, KUDISH P et al.: Human immunodeficiency virus type 1 mutations selected in patients failing efavirenz combination therapy. Antimicrob. Agents Chemother.[2000] 44(9]:2475-2484.
- JOLY V, DESCAMPS D, PEYTAVIN G et al.: Evolution of human immunodeficiency virus type 1(HIV-1] resistance mutations in nonnucleoside reverse transcriptase inhibitors[NNRTIs] in HIV-1-infected patients switched to antiretroviral therapy without NNRTIs. Antimicrob. Agents Chemother.[2004] 48(1]:172-175.
- Jena, A., Sachdeva, R. K., Sharma, A., &Wanchu, A.[2009]. Adverse drug reactions to nonnucleoside reverse transcriptase inhibitorbased antiretroviral regimen: A 24-week prospective study. Journal of the International Association of Physicians in AIDS Care, 8, 318–322.
- Paterson, D. L., Swindells, S., Brester, M., & Vergis, E. N.[2000]. Adherence to protease inhibitor therapy and outcomes in patients with HIV infection. Annals of Internal Medicine, 133, 21–30.
- Arendt, G., Nocker,D., VonGiesen, H. J., & Nolting, T.[2007].Neuropsychiatric side effects of efavirenz therapy. Expert Opinion on Drug Safety, 6, 147–154.
- Lochet, P., Peyriere, H., Lotth´e, A., Mauboussin, J. M., Delmas, B., & Reynes, J.[2003]. Long-term assessment of neuropsychiatric adverse reactions associated with efavirenz. HIV Medicine, 4, 62–66.
- O’Mahony, S. M., Myint, A., Steinbusch, H., & Leonard, B. E.[2005]. Efavirenz induces depressive like behaviour, increased stress response and changes in the immune response in rats. Neuroimmunomodulation, 12, 293–298.
- Rom˜ao, P. R. T., Lemos, J. C., Moreira, J., de Chaves, G., Moretti, M., Castro, A. A., et al.[2009]. Anti-HIV drugs nevirapine and efavirenz affect anxiety-related behavior and cognitive performance in mice. Neurotoxicity Research.
- Bickel, M., Stephan, C., Rottmann, C., Carlebach, A., Haberl, A., Kurowski, M., et al.[2005]. Severe CNS side effect and persistent high efavirenz plasma levels in a patient with HIV/HCV coinfection and liver cirrhosis. Scandinavian Journal of Infectious Diseases, 37, 520–252.
- Guti´errez, F., Navarro, A., Padilla, S., Ant´on, R., Masi´a, M., Borr´as, J., et al.[2005]. Prediction of neuropsychiatric adverse events associated with long-term efavirenz therapy, using plasma drug level monitoring. Clinical Infectious Diseases, 41, 1648–1653.
- Treisman, G. J., & Kaplan, A. I.[2002]. Neurologic and psychiatric complications of antiretroviral agents. AIDS, 16, 1201–1215.
- Hawkins, T., Geist, C., Young, B., Giblin, A., Mercier, R. C., Thornton,K., et al.[2005]. Comparison of neuropsychiatric side effects in an observational cohort of efavirenzand protease inhibitor-treated patients. HIV Clinical Trials, 6, 187–196.
- 28. Blanch, J., Corbella, B., Garcia, F., Parellada, E., & Gatell, J. M.[2001]. Manic syndrome associated with efavirenz overdose. Clinical Infectious Diseases, 15, 270–271.
- Fumaz, C. R., Mun˜oz-Moreno, J. A., Molt ´ o, J., Negredo, E., Ferrer, M. J. M. A., Sirera, J., et al.[2005]. Long-term neuropsychiatric disorders on efavirenz-based approaches: Quality of life, psychologic issues, and adherence. Journal of Acquired Immune Deficiency Syndromes, 38, 560–565.
- https://www.drugs.com/mtm/efavirenz.html
Supplier
Hubei widely chemical technology Co., Ltd.
Telephone186-02735115 18602735115
Websitehttp://www.hbwidely.cn
Shanghai Boyle Chemical Co., Ltd.
Telephone
Websitehttp://www.boylechem.com
J & K SCIENTIFIC LTD.
Telephone18210857532 18210857532
Websitehttps://www.jkchemical.com
3B Pharmachem (Wuhan) International Co.,Ltd.
Telephone 18930552037
Websitehttps://www.chemicalbook.com/ShowSupplierProductsList13285/0_EN.htm
Chembest Research Laboratories Limited
Telephone021-20908456
Websitehttp://www.BioChemBest.com
Capot Chemical Co., Ltd
Telephone+86 (0) 571 85 58 67 18
Websitehttp://www.capotchem.com/
Adamas Reagent, Ltd.
Telephone400-6009262 15618770481
Websitehttp://www.tansoole.com
Shanghai Hanhong Scientific Co.,Ltd.
Telephone021-54306202 13764082696
Websitehttps://www.hanhongsci.com
Chemsky(shanghai)International Co.,Ltd.
Telephone021-50135380
Websitehttp://www.shchemsky.com
China DongFan Chemical Co.,LTD
Telephone86-0571-85151182
Websitehttps://www.chemicalbook.com/ShowSupplierProductsList14819/0_EN.htm
Sinopharm Chemical Reagent Co,Ltd.
Telephone86-21-63210123
Websitehttp://www.reagent.com.cn
Wuhan Fortuna Chemical Co., Ltd
Telephone027-59207852 13308628970
Websitehttp://www.fortunachem.cn
Dalian Meilun Biotech Co., Ltd.
Telephone0411-62910999 13889544652
Websitehttp://www.meilunbio.com/
Acorn PharmaTech Co., Ltd.
Telephone025-58395930
Websitehttp://www.acornpharma.com
ShangHai YuanYe Biotechnology Co., Ltd.
Telephone 15026964105
Websitehttp://www.shyuanye.com
T&W GROUP
Telephone021-61551611 13296011611
Websitehttp://www.trustwe.com/
Beijing HuaMeiHuLiBiological Chemical
Telephone010-56205725
Websitehttp://www.huabeibiochem.com/
Shanghai T&W Pharmaceutical Co., Ltd.
Telephone+86 21 61551611
Websitehttp://www.trustwe.com
1of4
PROMPT×
PROMPT
The What'sApp is temporarily not supported in mainland China
The What'sApp is temporarily not supported in mainland China
Cancel
Determine